What Are the Anion Gap?
The anion gap is a computed result used to assist evaluate serum electrolytes and understand a person’s acid-base status. It looks at the main measured cationic ions and negative ions in the blood, especially sodium and chloride, with bicarbonate factored in the balance. Because not every ion is directly measured, the anion gap gives a clue about unmeasured ions that may be present in the blood.
Clinicians often use this number as a diagnostic marker during a medical assessment https://anion-gap-app417.hexaforgey.com/posts/how-to-operate-an-anion-gap-calculator-for-blood-chemistry-values when a person has an abnormal result on a blood chemistry panel or basic metabolic panel. It is not a standalone diagnosis. Instead, it supports guide clinical interpretation of a person’s electrolyte balance, possible systemic acidosis, and overall serum chemistry.
One reason the anion gap is so useful is that it can show a hidden change in anion concentration. If acids accumulate in the blood, the gap often rises. If certain proteins, measurement issues, or unusual conditions are present, the gap can fall. That is why the anion gap is both a screening test and an interpretive guide rather than a final answer by itself.
The anion Gap Formula and Calculator Inputs
This anion gap formula is easy:
Anion gap = sodium - (chloride + bicarbonate)
Some labs and calculators may use an alternate formula depending on whether potassium is included, but the typical modern formula leaves potassium out. That is why an Anion Gap Calculator is valuable: it can quickly perform the gap calculation once the correct lab inputs are entered.
To use the calculator correctly, you need values from a blood test or basic metabolic panel. The typical inputs are:
- Sodium Chloride Bicarbonate
These are part of routine serum electrolytes and are usually reported in milliequivalents per liter. The calculator then returns a calculated value that can be compared with the lab’s reference interval.
Because the anion gap reflects the difference between measured cations and measured anions, it indirectly estimates the amount of unmeasured ions in the serum. That is why the result can support a broader medical assessment of acid-base disorders. It is a practical way to spot whether the blood chemistry pattern fits metabolic acidosis or another imbalance.
Step-by-Step: How to Determine the Anion Gap
Here are the basic steps for calculation for finding the anion gap from common lab values:
- Locate the serum sodium value from the lab report. Find the serum chloride value. Locate the bicarbonate value. Combine chloride and bicarbonate together. Deduct that sum from sodium.
Example: When serum sodium is 140, serum chloride is 102, and bicarbonate is 24, then:
140 - (102 + 24) = 14
Here, the anion gap is 14. Whether it is considered normal depends on the lab’s reference range, the testing method, and sometimes the patient’s albumin level. That is why, a single number should always be considered alongside the rest of the laboratory result.
While using an Anion Gap Calculator, make sure the inputs come from the same draw and the same blood chemistry panel. Inconsistent values can distort the final interpretation. The calculator is only as accurate as the lab values entered into it, so reviewing the report carefully matters.
In practice, the question is not only “What is the number?” but also “What does this number mean in context?” This context includes the rest of the serum chemistry, the patient’s symptoms, and whether there is evidence of metabolic acidosis or another acid-base disorder.
What Is a Typical Anion Gap?
A healthy range for the anion gap can change by laboratory because different instruments and methods create different reference range values. In many settings, the normal anion gap is found in a relatively limited interval, but the exact cutoff should always be taken from the lab report.
The anion gap is also influenced by albumin, the main negatively charged protein in the blood. When albumin is low, the gap may appear reduced than expected even if no major acid-base problem is present. This is one reason clinicians may adjust their thinking using a adjustment factor for albumin in certain situations.
Because albumin affects the measured gap, a apparently normal result on a blood panel does not always rule out a clinically important problem. Likewise, a slightly outside value does not automatically mean disease. The full clinical assessment depends on the rest of the patient’s picture, including the salt balance, other tests, and symptoms.
In practice, the anion gap is most helpful when it is matched to the lab’s expected range and then evaluated for trends. A result that is near the upper end of normal may still matter if the patient has signs of acid buildup. That is why the anion gap remains a useful clinical marker in routine medical evaluation.
What Is a High Anion Gap Suggest?
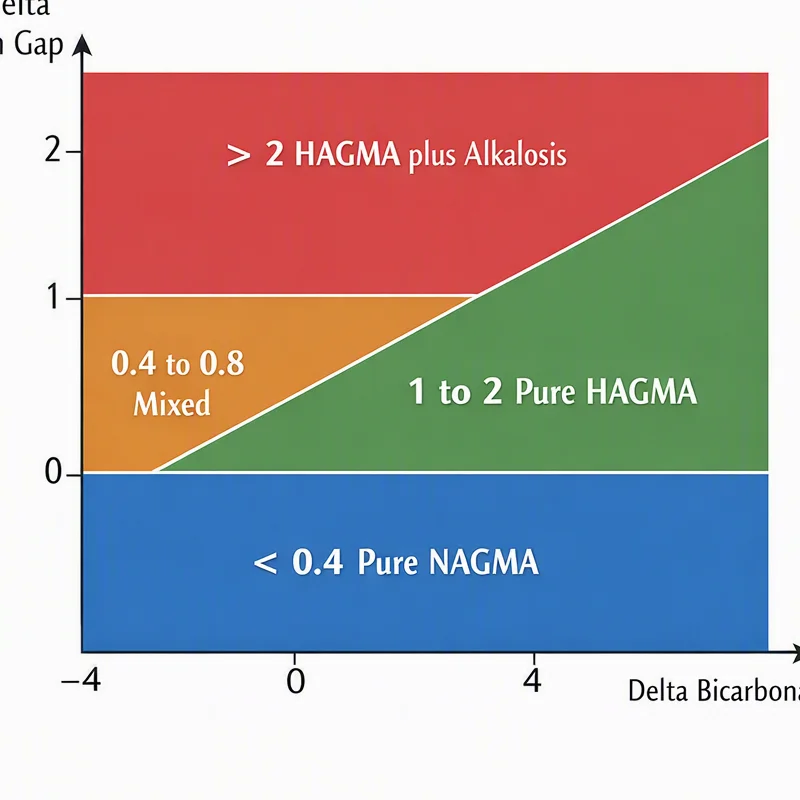
A raised anion gap often indicates that acidic substances or various negative substances have built up in the blood. This finding is often associated with metabolic acidosis. To put it simply, the measured bicarbonate decreases as it is utilized to buffer acids, while the gap increases because of increased undetected ions.
Two common drivers of a high anion gap are lactic acidosis and ketoacidosis. In lactic acidosis, the body builds up lactate, often because tissues are not getting enough oxygen or because of severe illness. In ketoacidosis, ketones increase, usually in settings such as diabetes, prolonged fasting, or severe carbohydrate deficiency.
A high gap can also appear in other forms of systemic acidemia. The key idea is that the blood holds extra acids that are not directly counted in the standard electrolyte measurements. The anion gap becomes an indicator that helps limit the possible cause.
For this reason, a high anion gap is not just a number; it is an indicator that needs follow-up. The following step is usually to assess the rest of the labs, the patient’s symptoms, and the likely source of the acid load. This finding is part of a broader clinical interpretation, not the final diagnosis.
What Does a Decreased Anion Gap Indicate?
A low anion gap is rarer than a high one, but it can still be meaningful. One major cause is hypoalbuminemia, or low albumin. Because albumin normally contributes negative charge, a drop in albumin can lower the calculated gap.
Another possible explanation is multiple myeloma, a condition that can alter the pattern of proteins in the blood and alter the measured balance of ions. In these cases, the low value may offer a clue that further evaluation is needed.
Sometimes a low value is not caused by disease at all. Lab error or a sample problem can produce an abnormal result that disappears when the test is repeated. Because of this, a very low number should be confirmed before drawing conclusions.
When the anion gap is low, clinicians usually look at the full blood chemistry panel and consider whether the patient has low albumin, a protein disorder, or a measurement issue. A low result may have clinical meaning, but it should always be interpreted carefully within the larger medical assessment.
Common Reasons That Affect the Anion Gap
Several conditions can change the anion gap up or down. A few stem from acid buildup, while others suggest altered proteins, kidney handling of acids, or measurement problems.
- Kidney failure can decrease acid excretion and lead to a high anion gap. Kidney disease may slowly impair acid-base regulation and alter the electrolyte pattern. Renal failure is an additional common setting in which acids build up and the gap rises. Toxins can create a high gap by bringing in unmeasured acids or altering metabolism. Salicylates are an major toxin category and can be involved in salicylate poisoning, which may distort acid-base status in different ways.
This matters because the anion gap is more than a mathematical result. It helps pinpoint the type of problem behind an abnormal laboratory result. A high value may prompt a search for acids, toxins, or decreased clearance. A low value may lead to consideration of low protein states or analytical issues.
In many cases, the anion gap is one piece of a larger picture that includes symptoms, kidney function, and the rest of the serum electrolytes. That is why recognizing the likely cause of an abnormal result is just as important as learning the formula itself.
When used well, the gap acts as a practical interpretive guide for clinicians and patients reviewing a screening test result. It can point toward hidden acid problems, help differentiate different forms of acidosis, and support more targeted testing when needed.
FAQs About the Anion Gap
How is calculated the anion gap from lab values?
Apply the anion gap formula: sodium minus the sum of chloride and bicarbonate. In other words, anion gap = sodium - (chloride + bicarbonate). You can also enter the same numbers into an Anion Gap Calculator to get a rapid calculation output. Make sure the values come from the same blood draw or BMP so the result matches the correct electrolyte levels.
What would be the normal anion gap range?
The expected range differs by laboratory, testing method, and the lab’s normal interval. Many labs use a fairly narrow interval, but there is no single number that fits every setting. For the most accurate medical interpretation, compare the result with the range listed on the report and consider whether albumin is normal.
Why can a high anion gap happen?
A elevated anion gap usually happens when extra acids build up in the blood, leading to acid buildup. Common examples include lactate acidosis and ketoacidosis. It can also occur with certain toxic substances or in kidney failure, where the body cannot remove acids effectively. The gap helps identify hidden acids that are not directly measured in routine labs.
May a low anion gap be a sign of a problem?
Yes. A reduced anion gap can be seen with low albumin, myeloma, or a laboratory error. Sometimes it is not clinically important, but it should not be ignored if it is unexpected or persistent. Rechecking the lab result and reviewing the rest of the blood panel can help determine whether the result is meaningful.
Should albumin be corrected when calculating the anion gap?
Often, yes, especially when albumin is low. Because albumin affects the measured balance of charges, a low albumin level can make the anion gap look falsely low. In those cases, clinicians may use a adjustment factor to better estimate the true gap. This improves assessment and helps avoid missing a real acid-base issue.