What Is the Anion Gap?
The anion gap is a derived value obtained from routine electrolytes tested on a blood chemistry panel. It serves to gauge the difference between the positive measured cations and the negatively charged unmeasured anions in the blood. Because this number indicates overall acid-base balance, it is a helpful screening tool for detecting a metabolic disturbance.
In everyday serum chemistry analysis, the anion gap is used to help explain whether an electrolyte imbalance is due to hidden acids, changes in protein levels, or another root cause. A lab result with an abnormal anion gap does not on its own give a diagnosis, but it can sharpen the differential and guide clinical decision making.

Most clinicians examine the anion gap alongside sodium, chloride, and bicarbonate, and sometimes potassium, depending on the calculation formula used. The result is an assessment of anion concentration that can help reveal conditions such as metabolic acidosis.
Ion Difference Formula with Potassium
The standard anion gap formula reads:
Anion gap = sodium - (chloride + bicarbonate)
If potassium is included, the formula changes to:
Anion gap = sodium + potassium - (chloride + bicarbonate)
This version includes another measured cation to the calculation. Since potassium is one of the serum electrolytes measured on many panels, some clinicians and older texts add it in the calculation. Some others leave it out because potassium is relatively low in concentration compared with sodium and may have a smaller effect on routine interpretation.
The main logic stays the same: the calculator compares principal cations against principal anions. Since the body contains many unmeasured anions, the anion gap acts as an indirect measure rather than a direct one. An Anion Gap Calculator performs this calculation https://anion-gap-app937.raidersfanteamshop.com/understanding-the-anion-gap-in-emergency-medicine quickly from the values in the patient sample.
How to Use an Anion Gap Calculator
An anion gap calculator is a useful tool for using the calculation formula correctly. To get started, gather the relevant lab values from the electrolyte panel or broader blood chemistry panel. The most common inputs are sodium, potassium, chloride, and bicarbonate.
Here are the basic calculation steps:
- Identify the serum electrolytes from the lab result. Check whether the formula used by your source includes potassium. Add sodium and potassium if applicable. Add chloride and bicarbonate. Subtract the total of chloride plus bicarbonate from the total of sodium plus potassium.
For example, if sodium is 140, potassium is 4, chloride is 104, and bicarbonate is 24, then the potassium-inclusive formula is 140 + 4 - (104 + 24) = 16. A calculator handles the arithmetic instantly, but understanding the logic is important for proper diagnostic interpretation.
Using the tool also reduces the risk of mistakes when reviewing multiple lab values in a busy clinical setting. It helps organize interpretation guide workflows and supports quicker recognition of acid-base disorders.
Normal Anion Gap Range and Its Meaning
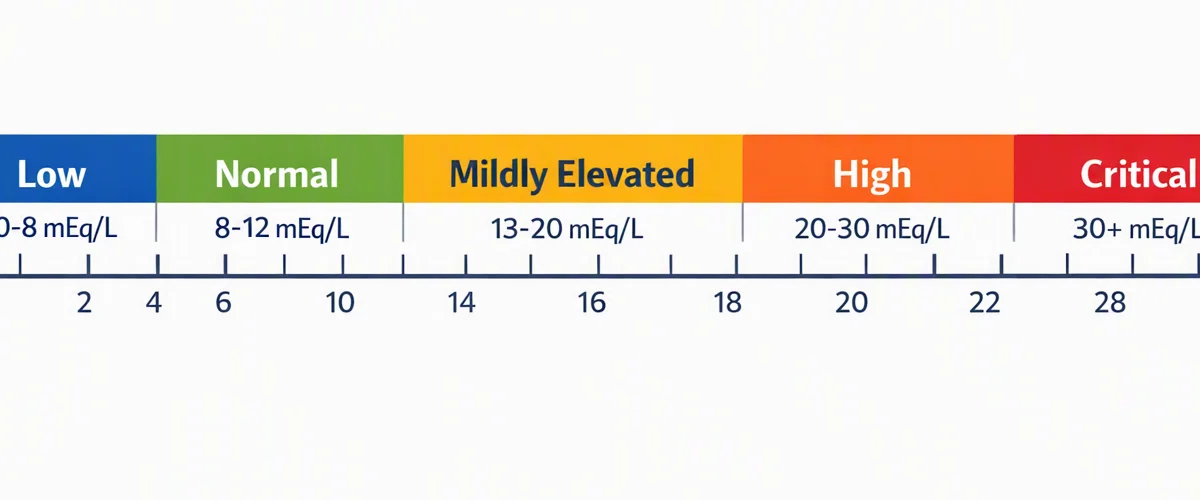
The expected range for anion gap depends on the method used and the laboratory normal interval. When potassium is excluded, the reference interval is usually lower than when potassium is included. That difference matters because the calculation method changes the usual baseline.
A high anion gap suggests that extra acids are accumulating in the blood. This often points to metabolic acidosis caused by processes such as excess lactate, ketone buildup, or impaired kidney function. A decreased anion gap is less common but can occur with hypoalbuminemia, laboratory issues, or unusual electrolyte patterns.
The anion gap is best interpreted as a indicator, not a stand-alone diagnosis. A result that sits within the expected range does not exclude disease, and a result outside the reference range should always be viewed in association with the patient sample, symptoms, and other chemistry findings.
When Potassium Is Included
Potassium inclusion varies with the formula variation in use and the practice of the laboratory or clinician. In some forms of clinical practice, potassium is included because it is a measured cation and because older teaching emphasized a more complete electrochemical picture.
In other situations, potassium is omitted to make easier routine interpretation. Since potassium is usually present at a much lower level than sodium, excluding it often does not change the overall clinical impression. That said, using the same approach throughout is essential when comparing results over time.
When reviewing an electrolyte panel, always verify which formula the report or calculator is using. If you switch between formula styles without noticing, the reference interval and the meaning of the result can appear inconsistent even when the underlying serum electrolytes have not changed.
Common Causes Behind an Abnormal Anion Gap
An abnormal anion gap often signals a change in the equilibrium between measured cations and unmeasured anions. The main reason for a high anion gap is metabolic acidosis, where acid buildup builds up or buffers are depleted.
Typical causes include:
- Lactic acidosis, as lactate rises due to reduced oxygen delivery to tissues or other metabolic stress Ketoacidosis, which may occur with diabetes, starvation, or alcohol-related metabolic disturbance Renal failure, where acid excretion declines and retained acids raise the gap
Albumin also plays a role because it is a major unmeasured anion. When albumin is low, the anion gap may be falsely low even if an acid-base problem is present. This is why the lab result must be interpreted in context rather than in isolation.
In what way Albumin Influences the Outcome
Hypoalbuminemia can strongly alter the anion gap because albumin adds to the pool of unmeasured anions. If albumin is reduced, the gap may look falsely normal or low even when there is a clinically important metabolic disturbance.
For this reason many clinicians use albumin correction to estimate a corrected anion gap. The goal is to adjust for the missing negative charge contributed by protein, especially albumin. This corrected value provides a more accurate picture of acid-base balance and can improve clinical interpretation.
In practice, a corrected value is especially useful when evaluating patients with chronic illness, inflammation, or fluid shifts that lower albumin. Without correction, a high-gap process can be underestimated, which may delay recognition of the underlying cause.
Worked Example: Calculating the Anion Gap with Potassium
Here is a basic worked calculation with the potassium-based formula.
Consider the following values from a serum chemistry panel:
- Serum sodium: 138 mEq/L Serum potassium: 4 mEq/L Chloride: 102 mEq/L Serum bicarbonate: 22 mEq/L
Apply the formula:
Anion gap = sodium + potassium - (chloride + bicarbonate)
Insert the values:
Anion gap = 138 + 4 - (102 + 22)
Anion gap = 142 - 124
Anion gap result = 18
If the lab’s reference range for the potassium-inclusive method is, for instance, 12 to 20, this result may be within the expected range. When the lab uses a different reference interval, the same number could be interpreted another way. This is why the formula and the reference range must always correspond.
If albumin is low, the corrected anion gap may be higher than the uncorrected value. Under those circumstances, the corrected value may more accurately show the true degree of metabolic disturbance.

Constraints and Clinical Interpretation
The anion gap is a valuable diagnostic tool, but it has important drawbacks. A single result cannot replace full clinical assessment, especially when the patient has complex illness, mixed disorders, or changing fluid status. The value should be reviewed with history, physical exam, and other lab data.
Testing error is another concern. Sample handling issues, incorrect specimen timing, or analyzer variation can affect the result. If the anion gap does not fit the overall picture, repeat testing or confirmatory evaluation may be needed.
Blood gas testing may also provide useful context, especially when assessing acid-base balance. A arterial blood gas can help clarify whether there is acidosis, alkalosis, or a mixed pattern. Used together, the blood gas and chemistry results improve the accuracy of diagnostic interpretation.
In the end, the anion gap should be viewed as a initial marker that suggests an possible cause rather than as a standalone diagnosis. It guides clinical decision making, but it does not replace a full workup.
FAQ: Anion Gap and Potassium
How do you calculate anion gap with potassium included?
Use the formula sodium + potassium - (chloride + bicarbonate). Input the serum electrolytes from the lab result into an Anion Gap Calculator or work out manually. The result reflects the gap between measured cations and unmeasured anions.
Why do some formulas include potassium and others do not?
Some formulas include potassium because it is a measured cation and part of the full electrolyte balance. Others omit it because the value is small compared with sodium and the simplified formula is easier for routine use. Both approaches can be valid if the same reference range and formula style are used consistently.
What is a normal anion gap when potassium is included?
The normal range depends on the lab’s reference range and the exact calculation formula. Potassium-inclusive values usually have a higher expected reference interval than potassium-excluded values. Always interpret the result using the same method that was used to calculate it.
Does low albumin change the anion gap result?
Indeed. Low albumin, or hypoalbuminemia, can reduce the measured anion gap because albumin is a major unmeasured anion. In that situation, albumin correction may reveal a more accurate corrected anion gap.
What does a high anion gap mean clinically?
A high anion gap often suggests a buildup of acids and is commonly associated with metabolic acidosis. Important causes include lactic acidosis, ketoacidosis, and renal failure. It is a clue that should be interpreted along with the rest of the clinical picture.