An https://anion-gap-reader194.cavandoragh.org/how-to-apply-an-anion-gap-calculator-for-blood-tests anion gap calculator is a practical diagnostic tool for reviewing renal failure and connected acid-base problems. In patients with kidney failure, alterations in electrolytes can indicate metabolic acidosis, assist in identifying the cause of acidosis, and guide next steps in clinical interpretation. Used correctly, the anion gap is more than a number; it is a sign to how well kidney function is preserving acid-base balance.
Because renal impairment changes the handling of acids and electrolytes, the result must be interpreted alongside serum chemistry, laboratory results, and the full medical assessment. That includes looking at serum sodium, serum chloride, serum bicarbonate, potassium, albumin, creatinine, and blood urea nitrogen. In other words, the calculation is only the initial step.
What the Anion Gap Measures
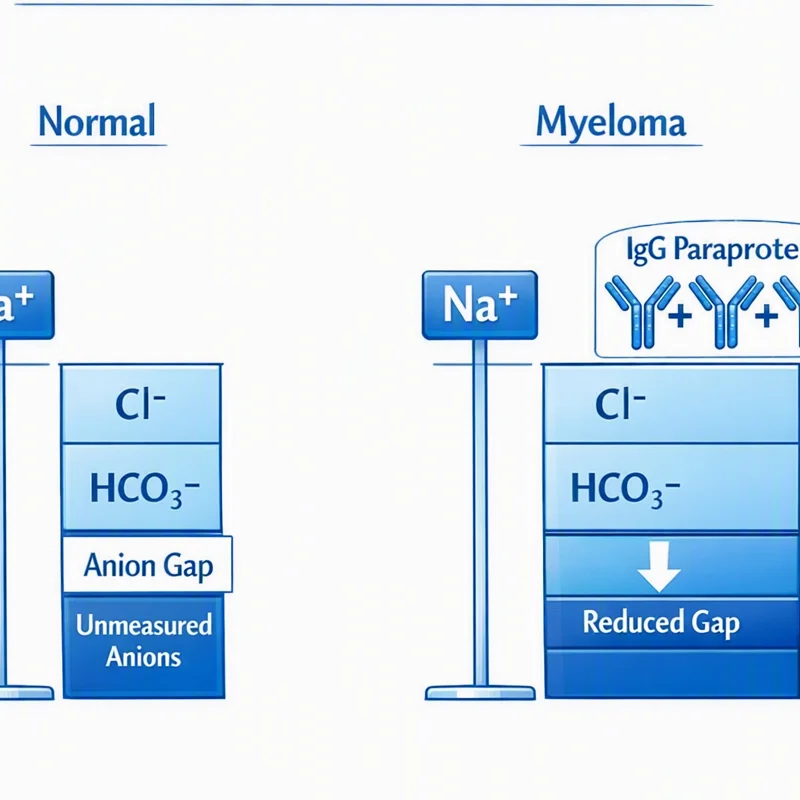
The anion gap calculates the discrepancy between recorded cations and recorded anions in the blood. It helps to detect unmeasured anions that are not directly listed on routine lab panels. In most situations, the calculation relies on serum sodium, serum chloride, and serum bicarbonate, with potassium sometimes included depending on the formula used.
This concept is useful because the body maintains electrical neutrality. If the measured electrolytes do not fully balance, the mismatch suggests hidden acids or other charged particles. That difference can point toward an electrolyte imbalance or a broader acid-base disorder.
Often, the anion gap shows the relationship between sodium on one side and chloride plus bicarbonate on the other. If chloride and bicarbonate shift in opposite directions, the gap changes. This is why the anion gap serves as a simple window into serum chemistry and overall acid-base balance.
In clinical practice, the value is especially important when looking for systemic acidosis. A widened gap suggests accumulation of acids or other unmeasured anions, while a normal gap suggests a different pattern of metabolic derangement. The interpretation depends on the reference range used by the laboratory and on the patient’s overall picture.
The reason the Anion Gap Is Important in Renal Failure
Kidney failure alters acid handling, acid excretion, and electrolyte control. As kidney function declines, acids that would normally be removed can build up, leading to metabolic acidosis. This makes the anion gap especially useful in people with kidney failure or progressive renal impairment.
A key reason is uremia. When the kidneys can no longer remove acid load efficiently, uremic toxins and other retained solutes lead to anion gap elevation. In advanced chronic kidney disease, this often causes a high anion gap metabolic acidosis. In more acute settings, acute kidney injury may trigger a similar pattern if filtration drops suddenly.
It matters because not every acidosis in renal disease is the same. A high gap often suggests retained acids, while a normal gap may indicate bicarbonate loss or impaired acid secretion without major accumulation of unmeasured acids. Distinguishing between high anion gap metabolic acidosis and normal anion gap metabolic acidosis helps narrow the differential diagnosis and influences treatment decisions.

In short, the anion gap is a practical way to connect kidney function with the patient’s acid-base disorder. It helps clinicians decide whether the acidosis is primarily due to retention of acid, loss of bicarbonate, or another overlapping process.
How to Work Out the Anion Gap
An anion gap calculator streamlines the calculation formula, but knowing the inputs is essential. Most tools rely on serum sodium, serum chloride, and serum bicarbonate. Some approaches also use potassium, though many modern approaches omit it because its contribution is usually small.
The usual formula is:
Anion gap = sodium − (chloride + bicarbonate)
If potassium is included, the formula becomes a slightly different version that incorporates potassium to the cation side. Either approach may be appropriate depending on local procedures and the laboratory’s reporting guidelines. The key is to apply the same approach consistently when interpreting laboratory results.
For instance, if the sodium level is 140, chloride level is 102, and bicarbonate level is 18, the anion gap is 20. That is often above the usual reference range and suggest a high gap state. If the calculator includes K, the number may go up slightly, but the overall clinical meaning usually remains similar.
The calculator is most effective when used alongside the patient’s signs and other laboratory tests. A decreased bicarbonate level on its own indicates acidosis risk, but the anion gap reveals whether the acidosis is likely due to excess acids, bicarbonate loss, or a combination of both. That makes this a valuable medical assessment instrument in renal disease.
Adjusting for Albumin in Kidney Disease
Albumin has a major effect on the measured anion gap because it is a anionic protein. When hypoalbuminemia is present, the anion gap can appear incorrectly normal or only slightly elevated, even when important acid retention exists. That is why albumin correction is so important in kidney disease.
In patients with chronic kidney disease or acute kidney injury, low protein levels may decrease the observed gap and obscure important pathology. The corrected anion gap helps adjust for this by estimating what the gap would be if albumin were normal. This gives a more accurate corrected value and improves clinical interpretation.
Albumin correction is especially important when renal failure coexists with inflammation, malnutrition, or protein loss. In those settings, a patient may have a worrisome acid load despite a seemingly limited gap. Without correction, the clinician may downplay the severity of the metabolic derangement.
Because albumin is a principal contributor to the body’s negative charge, a low albumin level can significantly alter the anion gap. Correcting for albumin does not substitute for the full evaluation, but it increases the accuracy of the picture and avoids missed diagnoses.
Elevated Anion Gap vs Typical Anion Gap Acidosis
Understanding the distinction between high anion gap metabolic acidosis and normal anion gap metabolic acidosis is crucial in renal disease. Each are forms of acid-base disorders, but they show different processes.
High gap acidosis usually means that extra acids are present. In renal disease, this may happen because the kidneys cannot remove acids effectively, leading to buildup of uremia-related solutes and other retained acids. Other causes include lactic acidosis and ketoacidosis.
Standard gap acidosis, sometimes called hyperchloremic acidosis, generally occurs when bicarbonate is lost or when acid is not excreted properly but without a large buildup of unmeasured acids. In renal impairment, this can appear initially or alongside tubular dysfunction. The chloride level often rises as bicarbonate falls, keeping the gap within the expected range.
Both patterns represent an acid-base disorder, but they suggest different cause of acidosis pathways. In clinical practice, that distinction matters because the diagnostic workup and treatment approach may differ. The anion gap is therefore a clue to the underlying chemistry, not just a marker of severity.
Common Causes of Increased Anion Gap in Renal Failure
In patients with renal failure, an increased gap often reflects more than one process. The leading contributors include chronic kidney disease, acute kidney injury, and retention of uremic toxins. As filtration falls, acids accumulate, and the anion gap rises.
Uremia is a classic trigger. Retained acids and organic anions are not fully measured on routine labs, so they increase the gap. In advanced kidney disease, this can serve as a major driver of metabolic acidosis.
Lactic acidosis is another key possibility. Poor tissue oxygen delivery, sepsis, shock, or severe illness can all increase lactate. In a patient with renal impairment, lactate clearance may be impaired, making the gap even more elevated.
Ketoacidosis should also be kept in mind, especially if there is diabetes, poor intake, or prolonged fasting. Ketone accumulation leads to high anion gap metabolic acidosis and can coexist with renal dysfunction. Because multiple causes can coexist, the observed gap may not reflect a specific diagnosis.
Medication effects, toxins, and mixed conditions may also play a role. That is why the anion gap should always be interpreted with the rest of the chemistry panel, symptoms, and the patient’s clinical story.
Understanding Findings and Next Clinical Steps
The most accurate clinical interpretation starts with the complete context. Low serum bicarbonate suggests a risk of acidosis, but the next step is to ask whether the gap is elevated, unremarkable, or misleading because of low albumin. The result should be reviewed alongside creatinine, blood urea nitrogen, and the degree of kidney function impairment.
An arterial blood gas can add valuable detail. It helps confirm the pH, respiratory compensation, and whether there is a mixed respiratory problem. This matters because renal disease can coexist with a respiratory disorder, changing the apparent acid-base pattern.
When the gap is elevated, evaluate the major causes of high gap acidosis first: retained uremic acids, lactic acidosis, ketoacidosis, toxins, or mixed disease. If the gap is normal but bicarbonate is low, consider bicarbonate loss, tubular dysfunction, or saline-related hyperchloremic acidosis. If albumin is low, apply albumin correction before deciding the result is truly normal.
In practice, a useful approach is to compare the anion gap with the bicarbonate level and the patient’s symptoms. Significant anion gap elevation with low bicarbonate supports a high-gap acidosis. Discordant values may suggest a mixed acid-base disorder and should prompt deeper evaluation. That may include repeat laboratory results, review of exposures, and reassessment of renal status.
Limitations of an Anion Gap Calculator
Although an anion gap calculator is valuable, it has important limits. The first is the reference range. Different laboratories use different analyzers and reporting methods, so a “normal” value in one setting may be abnormal in another. This is a form of laboratory variation that can affect interpretation.
The second limit is that the calculator estimates, rather than directly records, the amount of unmeasured anions. That means it can miss key information if the patient has more than one process at once. A mixed acid-base disorder may mask the expected pattern and make the gap appear less obvious than the underlying illness really is.
The delta gap can help detect these mixed patterns by comparing the shift in anion gap with the difference in bicarbonate. If the numbers do not change in a predictable way, there may be both the high-gap and normal-gap components at the same time. This is particularly important in renal failure, where acidosis from kidney dysfunction may be accompanied by vomiting, diarrhea, lactic acidosis, or ketoacidosis.
Another drawback is that the calculator cannot replace bedside assessment. It does not tell you the full cause, severity, or timing of disease. It is best viewed as an element of a broader medical assessment that includes exam findings, imaging when needed, and serial testing.
Frequently Asked Questions
What is an anion gap calculator used for in renal failure?
An anion gap calculator is used to recognize whether a patient with renal failure has metabolic acidosis, especially high anion gap metabolic acidosis. It helps clinicians separate retained acid from other causes of low bicarbonate and supports the overall evaluation of acid-base balance.
How do you calculate the anion gap from lab values?
The usual calculation uses serum sodium minus the sum of serum chloride and serum bicarbonate. Some formulas also include potassium. The exact method depends on the laboratory and the reference range used, so it is important to interpret the number in context.
Why should the anion gap be corrected for albumin?
Albumin correction is important because low albumin from hypoalbuminemia can make the gap look falsely typical. In kidney disease, this can mask significant acid accumulation. A corrected anion gap gives a more accurate corrected value for clinical interpretation.
What does a high anion gap mean in kidney failure?
A elevated gap in kidney failure often suggests the body is holding onto acids, usually from uremia and other uremic toxins. It may also indicate lactic acidosis, ketoacidosis, or an additional overlapping cause. The finding should be checked with creatinine, blood urea nitrogen, and an arterial blood gas.
Can renal failure cause normal anion gap metabolic acidosis?
Yes. Renal failure can result in normal anion gap metabolic acidosis, especially when bicarbonate is lost or when tubular acid handling is impaired without a major buildup of unmeasured acids. This is why both high anion gap metabolic acidosis and normal-gap patterns must be taken into account during the assessment of renal impairment.