What the Anion Gap Measures
The anion gap is a calculated value that helps clinicians look for problems https://anion-gap-estimator805.readspirex.com/posts/anion-gap-calculator-for-assessing-changes-in-anion-gap in electrolytes and general acid-base balance. It is not a direct measurement of a single substance. Rather, it indicates the relationship between major measured ions in the blood, especially sodium, chloride, and bicarbonate. Because the body maintains a tightly regulated buffer system, changes in this number can suggest an underlying metabolic acidosis or another form of electrolyte imbalance.
In plain language, the anion gap may show whether there are unmeasured acids in the bloodstream. Those acids can include organic acids produced during illness, poor perfusion, or altered metabolism. A lower or higher value is not a diagnosis by itself, but it can support laboratory interpretation and help identify the cause of a patient’s symptoms or abnormal serum electrolytes.
Albumin matters too. Because albumin is a negatively charged protein, it contributes to the usual gap seen on blood testing. If albumin is low, the anion gap may look falsely normal or only mildly elevated even when clinically important acids are present. That is why clinicians often consider albumin correction when reviewing results.
Understanding the anion gap is especially useful because it is part of routine metabolic panel analysis and can reflect changes in renal function, acid production, and clearance. It is one of the most practical ways to think about hidden acid buildup in the blood.
How an Anion Gap Calculator Works
An Anion Gap Calculator employs measured lab values to determine the gap promptly. The standard anion gap formula is usually:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some versions also incorporate potassium, but the sodium-based formula is the most commonly used. The calculator is simple, but the interpretation is not. A result must always be viewed in clinical context, because the same number can mean different things depending on symptoms, medications, hydration status, and related laboratory findings.
The calculator is helpful because it converts routine blood chemistry into a more meaningful signal. If sodium stays stable while chloride rises or bicarbonate falls, the calculated gap can decrease or change in a way that suggests altered acid handling. If bicarbonate drops and chloride does not fully compensate, the gap may rise, creating an elevated anion gap or high anion gap result.
Many people use the calculator as a quick tool for understanding a metabolic panel. But it should never be treated as a standalone diagnosis tool. The number is only one piece of the full evaluation, and it is most meaningful when paired with other serum electrolytes, glucose testing, and kidney-related markers.
A calculator can show the number, but only the full lab picture clarifies why the number changed.
Can Fasting Raise the Anion Gap?
Indeed, fasting can in some cases increase the anion gap, especially if it results in ketosis. When the body does not obtain enough carbohydrate from food, it shifts its fuel use toward fat. This produces ketone bodies, which are acidic. As ketone production increases, those acids can enter the bloodstream and cause a mild rise in the anion gap.
This pattern is often called starvation ketosis when it happens from reduced intake rather than diabetes. In many healthy people, the effect is limited and temporary. The kidneys and respiratory system usually help maintain acid-base balance, so the result may be a slight, sometimes compensated acidosis rather than severe illness.
That said, fasting does not affect everyone the same way. The size of the change depends on how long the fast lasts, how much carbohydrate is usually eaten, overall nutrition, blood glucose levels, and whether there are other medical problems. A brief fast for a lab test is much less likely to cause major shifts than prolonged fasting or severe calorie restriction.
In most cases, fasting-related ketosis causes only a small acid load. But when ketone production becomes substantial, the body may develop a more pronounced metabolic derangement with an increasing gap. This is why an abnormal result should be interpreted alongside symptoms and related labs, not in isolation.
When Going without food Is More Likely to Affect Results
Certain situations make fasting more likely to influence the anion gap. Dehydration is one of the biggest. When fluid intake is low, blood becomes more concentrated, and renal clearance of acids may be less effective. That can amplify the effect of ketosis or make abnormal values easier to detect.
Low carbohydrate intake also matters. If someone is already following a very low-carb approach and then fasts, the body may move more quickly into ketone formation. This can increase the amount of ketone bodies circulating in the blood, especially if the fast lasts long enough for stored glucose to become limited.
Prolonged fasting is more likely than short fasting to alter laboratory values. As fasting continues, the body shifts more deeply into fat metabolism and glucose conservation. That change in glucose metabolism can promote ketone production and, in some people, a measurable rise in the anion gap.
Blood glucose level is also important. If glucose is normal or low during fasting, the situation is usually more consistent with nutritional ketosis. If glucose is high, especially in a person with diabetes, the pattern may be much more concerning and could point toward a serious acid-base disorder.
Other factors can interact with fasting too. Vomiting, poor oral intake, infection, and certain medications may all affect hydration status and metabolic stability. The lab picture is often shaped by a combination of factors rather than fasting alone.
Other Frequent Causes of a High Anion Gap
Fasting-related changes are only one potential explanation for a high anion gap. Several other conditions can cause a similar pattern and should always be considered during laboratory interpretation.
Lactic acidosis arises when the body produces or clears too much lactic acid. This may occur with inadequate oxygen delivery, severe infection, intense physiologic stress, or some medications. It is a common cause of elevated acids in the blood and can noticeably change the anion gap.
Kidney disease can also increase the gap. When the kidneys cannot remove acids effectively, the body retains unmeasured acid compounds, widening the gap and disrupting acid-base balance. In this setting, renal function is a central part of the workup.
Diabetic ketoacidosis is a serious medical emergency in which insulin deficiency leads to severe ketone production and major metabolic acidosis. Although it shares a ketone-related mechanism with fasting ketosis, it is much more dangerous and usually causes a substantially larger laboratory abnormality.
Toxic alcohols such as methanol or ethylene glycol can also cause a high gap because their metabolism generates harmful acidic byproducts. These cases require immediate medical evaluation and are not related to ordinary fasting.
Other sources of elevated anion gap include certain poisonings and severe systemic illness, but the conditions above are among the most frequent and clinically important. This is why the gap should always be interpreted with the whole picture in mind, not as a standalone finding.
Signs Requiring Prompt Care
Most mild fasting-related changes do not lead to major symptoms, but some warning signs should never be ignored. If abnormal results are accompanied by nausea, vomiting, confusion, or shortness of breath, quick medical care is important.
These symptoms may reflect increasing metabolic acidosis, substantial dehydration, infection, or another urgent condition. Shortness of breath may reflect the body attempting to compensate for acid buildup by altering breathing patterns. Confusion can suggest that the metabolic disturbance is altering brain function or that another urgent problem is present.
Because fasting can overlap with illness, a symptom review matters as much as the numbers. If the person has diabetes, kidney problems, or repeated vomiting, an elevated anion gap deserves quicker evaluation. One lab value should never be used to dismiss concerning symptoms.
If there is severe weakness, inability to keep fluids down, chest discomfort, or worsening mental status, the situation may require immediate assessment. The purpose of the anion gap is to detect problems early, not to delay care when symptoms point to something more serious.
How to Interpret Values With Clinical Guidance
Interpreting the anion gap correctly takes more than comparing the result to a reference range. Different laboratories use slightly different methods, and the expected range can vary depending on the analyzer and whether potassium is included. That is why the same result may be viewed differently across settings.
Clinicians often look at the anion gap together with albumin correction. If albumin is low, the corrected value may reveal a hidden elevated gap that would otherwise appear less impressive. This step is especially important when evaluating possible metabolic acidosis in people with ongoing health problems, systemic inflammation, liver disease, or poor nutrition.
The result should also be placed into the larger picture of acid-base balance. A person can have a raised gap with partial respiratory compensation, a normal gap with bicarbonate loss, or a mixed disorder. Reviewing these patterns often requires the full comprehensive metabolic panel along with other tests and the clinical story.
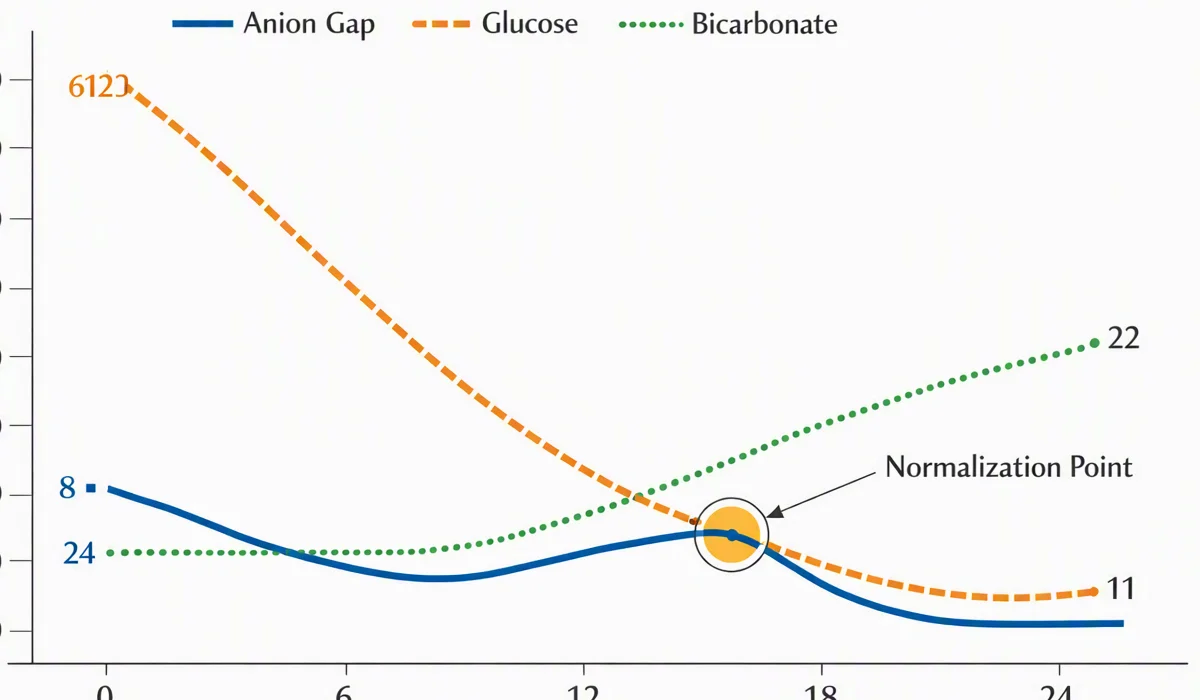
An Anion Gap Calculator can be a useful starting point, but it cannot determine the cause on its own. The question is not only whether the number is high, but why it is high, how high it is, and whether the rest of the test results fits with fasting, ketosis, dehydration, kidney disease, or another process.
In practice, clinicians may also consider the patient’s hydration status, glucose metabolism, and recent diet. A modest shift after fasting may reflect a benign, temporary change. A larger or persistent elevation deserves more investigation, especially if there are symptoms or an abnormal comprehensive metabolic panel.
FAQ About Fasting and the Anion Gap
Can fasting cause a high anion gap?
Yes. Fasting can cause a high anion gap if it leads to ketosis and ketone body buildup. This usually happens when the body shifts toward fat breakdown and produces more acidic byproducts. In many people, the rise is mild, but it should still be interpreted in clinical context.
How extended does fasting need to last to affect the anion gap?
This effect depends on fasting length, recent eating habits, hydration level, and overall condition. A brief fast may have a small impact, while a longer fast is more likely to increase ketone production and shift lab values. There is no universal threshold that applies to everyone.
Is a small rise in anion gap during fasting dangerous?
Not always. A small rise can occur with fasting ketosis and may not be dangerous if the person feels well and other labs are normal. However, a rising gap with symptoms, low bicarbonate, or abnormal blood glucose should be reviewed by a clinician.
What is the difference between fasting ketosis and diabetic ketoacidosis?
Starvation ketosis usually occurs from reduced carbohydrate intake and tends to be less severe. Diabetic ketoacidosis happens when there is insufficient insulin, leading to marked ketone production, dehydration, and serious metabolic acidosis. Diabetic ketoacidosis is an emergency and is not the same as ordinary fasting ketosis.
Should I stop fasting if my anion gap is abnormal?
It depends on the cause and your symptoms. If the abnormal result is small and you feel well, a clinician may simply want repeat labs or further information. If you have nausea, vomiting, confusion, shortness of breath, high blood glucose, or a markedly elevated gap, you should seek medical evaluation right away rather than continue fasting.