What Anion Gap Means and Why It Is Important
The anion gap is a practical lab-derived value used to detect the cause of metabolic acidosis and other imbalances in electrolytes. In the https://telegra.ph/What-Triggers-Normal-Anion-Gap-Metabolic-Acidosis-08-30 emergency department, it serves as a fast triage tool for acid-base balance problems and helps clinicians focus a broad differential into a streamlined diagnostic algorithm.
An anion gap calculator is helpful because the underlying concept is simple, but the interpretation is not. A patient may present with an apparently mild metabolic derangement, yet the pattern of serum electrolytes can reveal severe illness such as lactic acidosis, ketoacidosis, toxic ingestion, or renal failure. The gap represents the difference between measured cations and measured anions, which reflects unmeasured anions in the blood.
For emergency medicine, the anion gap is not just a number. It is a piece of clinical decision support that helps identify whether the patient likely has high anion gap metabolic acidosis, normal anion gap metabolic acidosis, or another acid-base disorder instead. It also guides whether to obtain additional studies such as a venous blood gas, lactate, ketones, toxicology testing, or an osmolar gap.
How to Calculate the Anion Gap
The typical anion gap formula uses the major measured electrolytes: sodium, chloride, and bicarbonate. A common version is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Potassium is sometimes included in laboratories and references, but in urgent practice, the sodium-based formula is used most often because it is straightforward, rapid, and widely available on the basic metabolic panel. The result indicates the amount of anion deficit from unmeasured ions.

Example: if sodium is 140, chloride is 104, and bicarbonate is 20, the calculation is 140 − (104 + 20) = 16. That value may be within normal limits or mildly elevated depending on the lab reference range and the patient’s clinical context.
An anion gap calculator streamlines this diagnostic calculation, limiting manual errors during time-sensitive critical care evaluation. It also helps clinicians quickly compare sequential results from an electrolyte panel when monitoring a patient’s response to treatment.
Using the Anion Gap Calculator in acute care
In acute care, the calculator is particularly valuable when a patient has unexplained tachypnea, altered mental status, hypotension, vomiting, dehydration, or concern for toxicity. It is typically used alongside the basic metabolic panel, point-of-care testing, and occasionally blood gas analysis.
Rapid testing can provide rapid sodium, chloride, and bicarbonate values that allow clinicians to identify metabolic abnormalities early. This matters when the patient may be deteriorating and decisions about fluids, insulin, bicarbonate, antidotes, or dialysis need to be made promptly.
Practical use in the ED often follows this sequence:
- Assess the lab results and calculate the anion gap. Determine whether the patient has metabolic acidosis on a venous blood gas or arterial sample. Assess whether the pattern suggests elevated anion gap acidosis or non-gap metabolic acidosis. Pursue confirmatory tests such as lactate, beta-hydroxybutyrate, ketones, renal function, or toxicology studies.
The value of the calculator is not in isolation, but in the way it improves result interpretation and supports early recognition of dangerous disease. In a fast-paced ED workflow, it is one of the most efficient ways to screen for major acid-base pathology.
Standard, Elevated, and Reduced Anion Gap Results
A normal anion gap usually implies that any acidosis present is caused by bicarbonate loss or chloride retention rather than by build-up of unmeasured acids. However, “normal” depends on the lab technique and normal range, so clinicians should always read the value using site standards.
Increased anion gap metabolic acidosis suggests too much unmeasured acids in the circulation. This is the result that often triggers urgent evaluation for lactic acid buildup, ketotic acidosis, toxic alcohols, and renal failure. It is a key signal in medical evaluation when a patient appears ill or has worrying vital signs.
A reduced anion gap is less common and can be missed. It may occur with severe albumin deficiency, laboratory artifact, or occasionally other less common clinical conditions. Although a low value is not usually the main urgent issue, it should prompt review of the test result and the broader acid-base problem.
For practical interpretation, the anion gap should be seen as a recognition aid rather than a single diagnosis. The presence of a normal or abnormal gap helps direct the next step in the diagnostic pathway, not replace it.
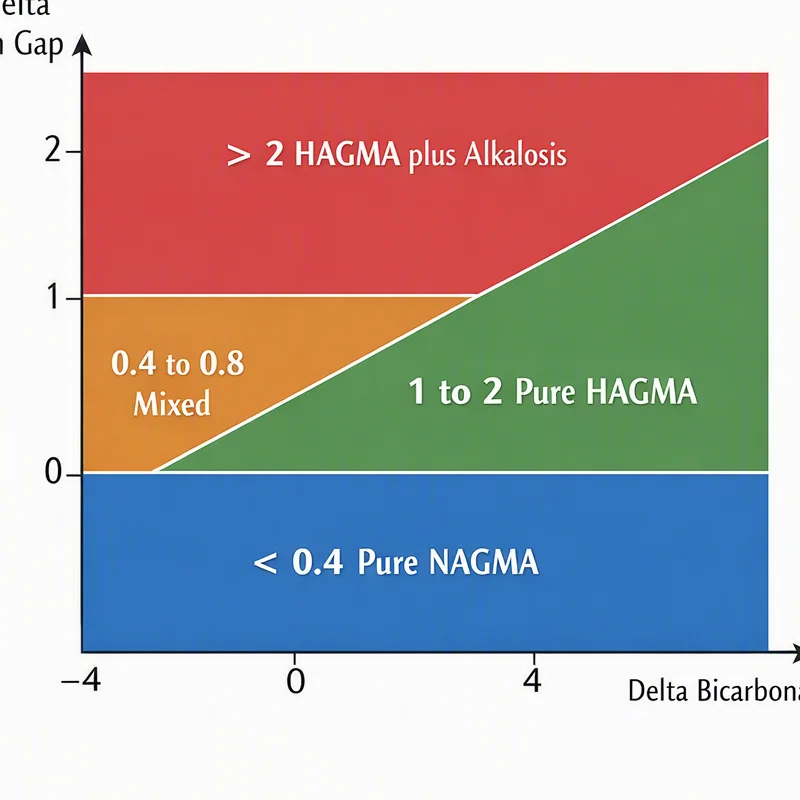
Typical Causes of a Increased Anion Gap
Various conditions can result in high anion gap metabolic acidosis, and the emergency provider should focus on rapid rule-out of life-threatening causes. The main and most important include lactic acidosis, ketoacidosis, and exposure to toxic alcohols.
Lactic acidosis often arises in shock, hypoperfusion, seizures, severe infection, or tissue ischemia. In the ED, this is a top concern in patients with concern for sepsis, hypotension, or respiratory compromise. The anion gap may rise as lactate accumulates and depletes bicarbonate during buffering.
Ketoacidosis occurs when ketone bodies build up as organic acids. Diabetic ketoacidosis is the typical emergency presentation, but starvation or alcoholic ketosis can also play a role. The bicarbonate level often decreases substantially, and the anion gap rises because ketones are unmeasured anions.
Toxic alcohols are another major cause of a high gap. Ethylene glycol and methanol are especially important because they can result in serious organ injury and may initially present with nonspecific symptoms. In these cases, the anion gap may rise later in the course, so timing matters. An elevated gap with suspicion of ingestion should prompt consideration of an osmolar gap and immediate toxicity screening.
Other causes may exist, but these three are the emergency priorities because they are urgent and potentially reversible with early intervention.
Typical Causes of Normal Anion Gap Acidosis
Normal anion gap acidosis is often linked to loss of bicarbonate or limited acid excretion. A typical lab pattern includes a drop in bicarbonate with a compensatory rise in chloride, creating hyperchloremic metabolic acidosis.
Diarrhoea is one of the most common causes. Gastrointestinal bicarbonate loss can lower serum bicarbonate while chloride goes up to maintain electrical neutrality. This is a classic example of how the chloride movement helps maintain balance on laboratory reports while the patient remains metabolically acidotic.
Renal tubular acidosis is also an important cause. With this disorder, the kidneys cannot properly acidify urine or retain bicarbonate, leading to continued acidosis despite a normal anion gap. It is important to recognize this because it may suggest chronic kidney disease or another underlying renal problem rather than a brief illness.
Normal anion gap acidosis can also occur after large amounts of saline, though the primary causes to consider to keep in mind remain diarrhoea, renal tubular acidosis, and renal losses of bicarbonate. Careful review of fluids, medications, and recent illness helps tell these patterns apart.
How Albumin Influence the anion gap
the protein albumin acts as the key unmeasured anion in plasma, so a low albumin level can spuriously reduce the anion gap. This is important because a patient may have a meaningful acidosis that appears not as severe on the initial calculation.
For this reason clinicians often use a adjusted anion gap when low albumin is present. A typical approach is to adjust the measured gap upward when albumin is below normal, allowing detection of hidden excess acids. The exact correction method may vary by institution, but the principle is the same: low albumin can conceal a dangerous elevation.
This adjustment is especially relevant in critical care and in patients with hepatic disease, malnutrition, inflammation, or chronic illness, where low albumin is frequent. Without correction, the anion gap may downplay the true degree of metabolic derangement.
In practice, a corrected calculation strengthens laboratory interpretation and can uncover a masked high gap when the raw result appears misleadingly normal. For that reason the anion gap calculator is most useful when paired with albumin data rather than used alone.
Step-by-Step Assessment in the ED
Interpreting the anion gap in the emergency department should use a clear approach. The goal is to detect the underlying acid-base disorder rapidly and decide whether immediate treatment is needed.
Step 1 — Confirm the chemistry values. Assess sodium, chloride, and bicarbonate from the basic metabolic panel or point-of-care source. Make sure the result is plausible and not obviously affected by laboratory error.
Step 2 — Establish whether the patient has metabolic acidosis on a venous blood gas or other blood gas measurement. A low bicarbonate alone is not enough; pH and respiratory compensation help define the full picture.
Step 3 — Label the gap as normal, elevated, or low. If elevated, think first about lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. If normal, consider bicarbonate loss or chloride excess.
Step 4 — If the presentation suggests ingestion, check the osmolar gap. An elevated osmolar gap with metabolic acidosis raises suspicion for toxic alcohol exposure, especially when clinical findings are unclear.
Step 5: Combine all findings with the story. The same lab result means something different in a stable patient with mild diarrhea than in a hypotensive patient with altered mentation and respiratory distress.
This stepwise method is essentially a bedside diagnostic algorithm that pairs the calculator with patient status, blood gas data, and additional labs. It is a practical example of metabolic evaluation in real-time care.
Constraints and Caveats of the Calculator
Like any diagnostic calculation, the anion gap calculator has limitations. Small differences in lab methods can create measurement variation, so the exact normal range can vary between institutions and analyzers.
Laboratory error can also mislead interpretation. Hemolysis, specimen handling issues, or inconsistent repeat values may produce a result that does not fit the clinical picture. When the number and the patient do not match, repeat testing and correlation with other data are essential.
The calculator does not replace clinical context. A small increase may still be very important in a poisoned, unstable patient, while a higher result may be long-standing or somewhat compensated in a patient with known kidney disease. The anion gap should therefore be interpreted as part of the full clinical context rather than as a standalone prompt.
Additional pitfalls include failing to account for albumin, assuming every high gap is due to one cause, or failing to look for a mixed disorder. The most accurate interpretation usually comes from pairing the anion gap with arterial blood gas results, renal labs, ketones, lactate, and toxin screening when indicated.
When to Escalate Evaluation or Treatment
Escalate without delay when the anion gap suggests a serious condition such as sepsis, renal failure, or poisoning. These are not just lab abnormalities; they are urgent emergencies that can worsen quickly without treatment.
In suspected sepsis, an elevated gap plus elevated lactate or hemodynamic instability should prompt rapid resuscitation, cultures, antimicrobial therapy, and source evaluation. In renal failure, worsening acidosis may require nephrology input, close electrolyte monitoring, and possible renal replacement therapy depending on the overall picture.
For suspected poisoning, especially with toxic alcohols, ethylene glycol, or methanol, do not hold off for confirmatory results if the clinical suspicion is high. The combination of acidosis, elevated gap, and possible osmolar gap can justify urgent antidotal therapy and consultation with toxicology.
Escalation is also appropriate when the patient has worsening mental status, respiratory fatigue, shock, or rapidly changing laboratory values. The calculator should guide the next action, not hold it up.
Frequently Asked Questions
What is the anion gap calculator used for?
The anion gap calculator is used to quickly estimate the anion gap from serum sodium, chloride, and bicarbonate values. In emergency medicine, it helps clinicians recognize metabolic acidosis, differentiate acid-base disorders, and decide whether further evaluation for lactic acidosis, ketoacidosis, toxic alcohols, or renal failure is needed.
What’s the typical range for the anion gap?
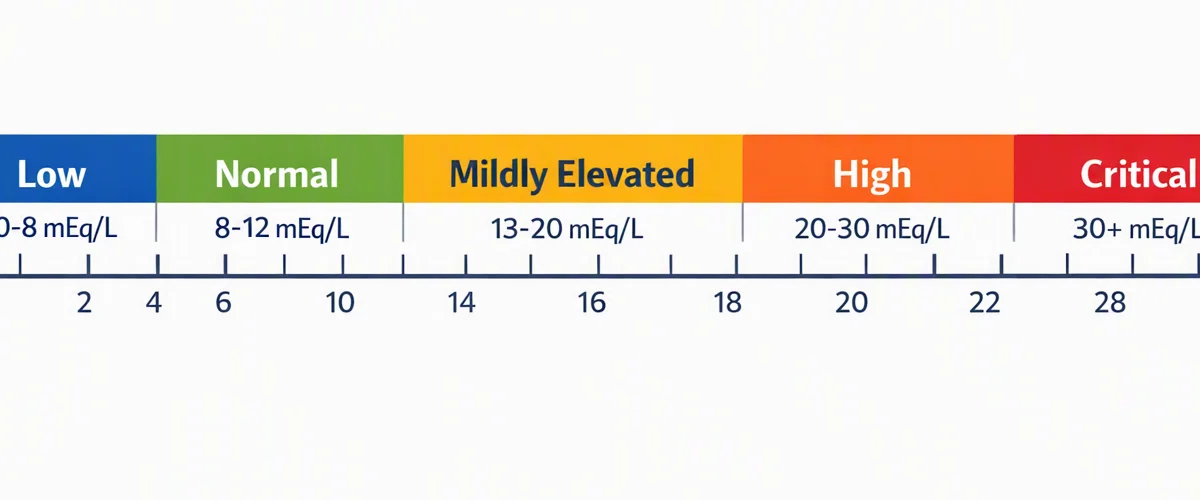
The usual range depends on the laboratory method and reference standard used by that facility. Because assay methods vary, clinicians should interpret the value using the lab-specific range rather than relying on a one universal threshold. In practice, the result is best understood in along with the patient’s symptoms, bicarbonate level, and overall acid-base balance.
How do you calculate a corrected anion gap for albumin?
To estimate a corrected anion gap, clinicians modify the measured result upward when albumin is low because hypoalbuminemia can hide a true elevation. The exact correction formula can vary, but the goal is the same: account for the effect of low albumin on the gap so that significant metabolic acidosis is not missed. This is especially useful in patients with long-term illness, liver disease, or critical illness.
What causes a high anion gap in emergency medicine?
The most important causes of high anion gap metabolic acidosis in emergency medicine include lactic acidosis, ketoacidosis, and toxic alcohols such as ethylene glycol and methanol. Other important causes include sepsis and renal failure. The anion gap should be interpreted with blood gas results, lactate, ketones, renal studies, and the patient’s overall presentation.
When should an osmolar gap be checked with anion gap results?
An osmolar gap should be checked when there is concern for ingestion, especially if the patient has unexplained acidosis, altered mental status, or a history that suggests possible exposure to toxic alcohols. It is particularly useful when evaluating possible ethylene glycol or methanol poisoning. In the ED, the osmolar gap adds another layer of toxicity screening to the broader metabolic evaluation.