How the anion gap Evaluates
The anion gap is a computed value used to evaluate electrolyte balance and support assessment of acid-base status. It helps clinicians interpret a laboratory result by calculating the difference between recorded cations and measured anions in the blood. Because routine chemistry panels do not measure every charged particle, the anion gap offers insight into unmeasured anions that may be present during a metabolic disturbance.
An anion gap calculator is a practical diagnostic tool for reviewing blood chemistry quickly. It is especially useful when a patient has an electrolyte imbalance, since small shifts in sodium, chloride, bicarbonate, and related values can signal an underlying acid-base disorder. In simple terms, the calculation helps show whether the blood has an excess of acids, an excess loss of base, or a pattern that fits electrolyte shift physiology.
The anion gap is not a diagnosis by itself. It is part of broader acid-base analysis and should be interpreted alongside the full electrolyte panel, the serum bicarbonate level, and other clinical findings. Used well, it turns a basic chemistry snapshot into a more meaningful picture of acid-base balance.
How Chloride Shift Impacts the Anion Gap
The chloride shift refers to the shift of ions that helps preserve electroneutrality in body fluids. In clinical interpretation, shifts in chloride often occur in response to alterations in bicarbonate. When bicarbonate falls, chloride may rise to maintain balance, which can keep the anion gap near normal even when an acid-base disorder is present.
This relationship is important because the chloride shift can obscure or reveal a metabolic problem. For example, if bicarbonate is lost through the kidneys or gastrointestinal tract, the body may preserve or increase chloride. The result is a pattern of normal anion gap acidosis, also called hyperchloremic acidosis. In this setting, the anion gap may not rise, even though the patient has clear metabolic acidosis.
By contrast, if acids accumulate and bicarbonate falls without a matching chloride increase, the anion gap rises. That pattern is more indicative of high anion gap acidosis. Understanding the chloride shift helps distinguish whether the chemistry reflects a rise in acids, a depletion of base, or a compensatory change in the buffer system.
For that reason, an anion gap calculator is especially valuable when reviewing chloride level changes. It helps relate the raw numbers to the underlying physiology and improves recognition of a true anion deficit versus a mere compensatory shift.
Anion Gap Formula and Calculator Inputs
The standard anion gap calculation uses sodium, potassium, chloride, and bicarbonate. Many clinicians use the simplified formula:
Anion gap = Sodium − (Chloride + Bicarbonate)Some versions also include potassium as well:
Anion gap = (Sodium + Potassium) − (Chloride + Bicarbonate)Either approach approximate the relationship between measured cations and anions. The calculator input values generally come from standard serum electrolytes or a chemistry panel. Because each lab may report slightly different units or reference intervals, the exact reference range should always be interpreted in context.
In practical use, the calculator requires accurate values for:
- Sodium, the major measured cation Potassium, sometimes included in the formula Chloride, a primary measured anion Bicarbonate, often reported as CO2 on chemistry panels
These numbers show the patient’s current blood chemistry and help estimate whether there are extra unmeasured anions contributing to the result. A helpful way to think about the calculation is that it calculates the gap left behind by anions not listed directly on the panel.
Used correctly, the anion gap calculator provides a quick diagnostic calculation that supports bedside decision-making. However, it should always be reviewed as part of the full clinical picture rather than treated as a standalone answer.
Typical Values and Adjusted Anion Gap
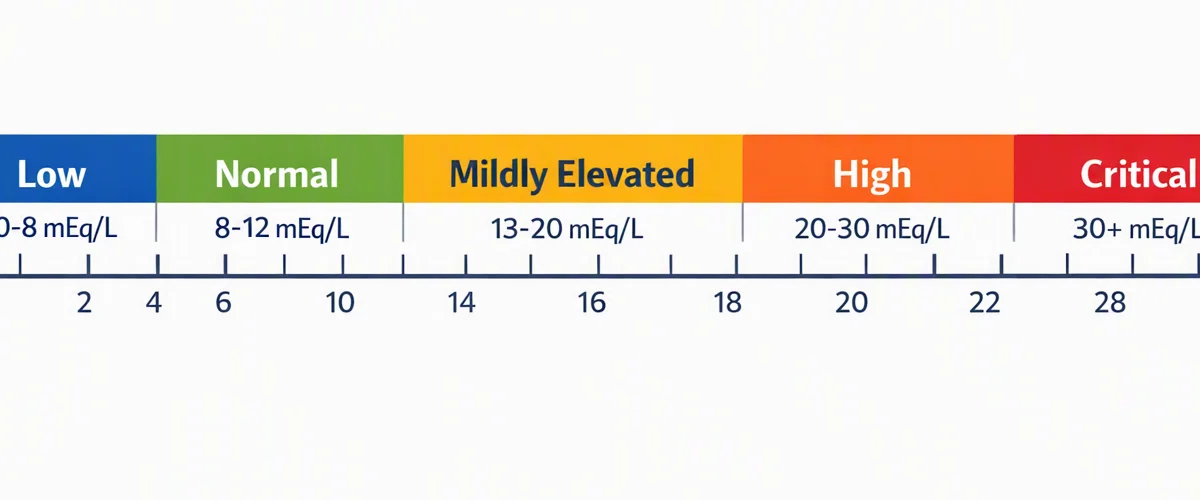
A typical normal anion gap differs slightly by laboratory technique and whether potassium is counted. Many clinicians view as a value around 8 to 12 mEq/L normal when potassium is not included, though the exact range should correspond to the lab’s reference range. A normal result does not always exclude illness; it may simply show that the electrolyte pattern is even in a way that does not elevate the gap.
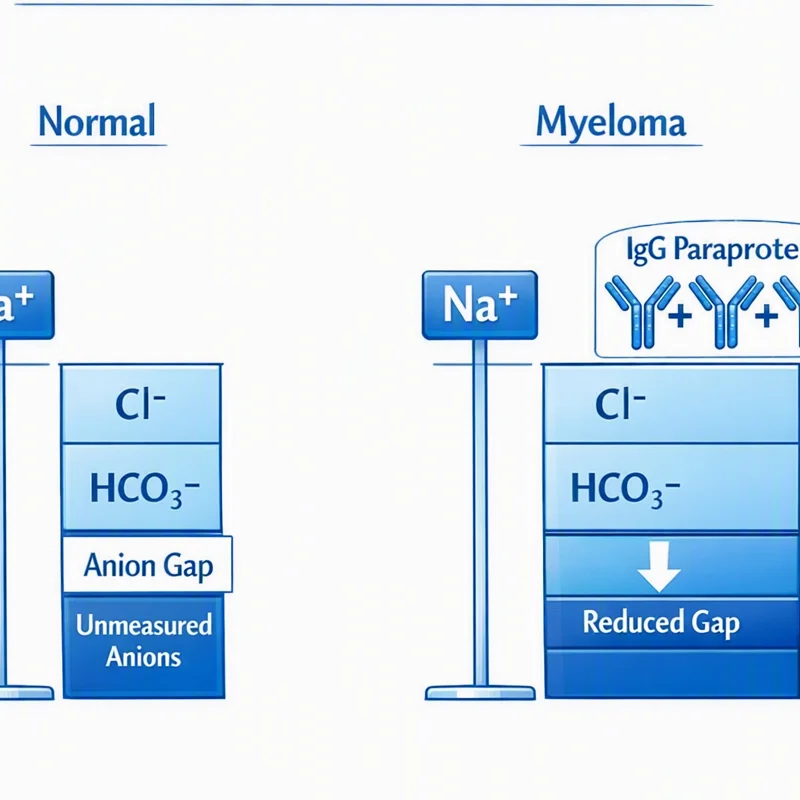
Albumin is a important unmeasured anion and has a significant effect on the anion gap. When albumin is low, the measured anion gap may appear falsely normal or low even if acids are present. This is why albumin correction matters so much in interpretation. In hypoalbuminemia, the corrected value can expose hidden metabolic problems that the unadjusted number overlooks.
A corrected value calculates what the anion gap would be if albumin were normal. This is useful because low albumin reduces the anion contribution from the protein fraction, creating an apparent anion deficit. Without adjustment, a patient with serious acid retention may seem less abnormal than they truly are.
Albumin correction is especially important in hospitalized patients, malnutrition, liver disease, or inflammation, where hypoalbuminemia is common. In these settings, the corrected value gives better clinical interpretation than the raw number alone. It can also help avoid missing a mixed acid-base disorder.
High Anion Gap vs Normal Anion Gap Disorders
Metabolic acidosis is the broad category most often assessed with the anion gap. The main distinction is whether the gap is increased or remains normal. A high anion gap acidosis implies that acids or acid equivalents have accumulated, increasing the amount of unmeasured anions in the blood.
Common causes of high anion gap acidosis include lactic acidosis, ketoacidosis, and renal failure. In each case, the body is holding on to or producing acids faster than they can be removed or buffered. The anion gap rises because bicarbonate is consumed while accompanying anions remain present in circulation.
A normal anion gap acidosis, on the other hand, usually reflects bicarbonate loss with a corresponding rise in chloride. This is where the chloride shift becomes important clinically. The chloride increase helps preserve electroneutrality, but the tradeoff is a lower bicarbonate concentration and a persistent acidosis without a widened gap.
Recognizing the difference matters because the causes and treatment strategies differ. High-gap disorders often prompt evaluation for toxic ingestion, tissue hypoxia, or severe metabolic crisis. Normal-gap disorders more often suggest gastrointestinal bicarbonate loss, renal tubular problems, or other patterns of chloride-related compensation.
Understanding Results in Clinical Context
This anion gap should be read together with the complete clinical picture, not on its own. An arterial blood gas aids identify whether the patient has low pH, alkalemia, or a mixed disorder. Meanwhile, serum electrolytes reveal whether alterations in chloride, bicarbonate, or sodium explain the gap.
One useful concept is the delta gap, which measures the elevation in anion gap to the drop in bicarbonate. This can help identify mixed acid-base problems. For example, if the gap is elevated above expected, there may be an additional metabolic alkalosis or chronic respiratory process. If the change is lower than expected, there may be a concurrent normal-gap acidosis.
Interpretation in practice becomes more useful when the anion gap is viewed as part https://rentry.co/wk5snvz3 of a broader acid-base analysis. A patient may have a high-gap metabolic picture on chemistry results, but the arterial blood gas may reveal compensation, overlap, or a second process. For this reason the anion gap calculator should assist, not replace, clinical reasoning.
When reviewing a serum bicarbonate result, it is also important to note whether the bicarbonate drop matches the chloride rise. If chloride is elevated while bicarbonate is low, the pattern may support a normal anion gap acidosis. If chloride is not elevated and bicarbonate is low, an accumulation of acids is more likely.
Common Causes of Abnormal Results
Irregular anion gap results often suggest a specific acid-base disturbance. A increased gap may suggest lactic acidosis, ketoacidosis, renal failure, or exposure to toxins. These conditions increase acid load or decrease acid clearance, which raises anion concentration from unmeasured acids.
Lactic acidosis usually occurs when tissue oxygen delivery is impaired or when metabolism shifts toward anaerobic pathways. Ketoacidosis may arise in diabetes, starvation, or alcohol-related states. Renal failure reduces the kidney’s ability to excrete acids and regenerate bicarbonate, leading to a progressively higher gap over time.
Normal-gap abnormalities are often caused by gastrointestinal loss of bicarbonate, such as diarrhea, or renal causes that lose bicarbonate. In these situations, chloride goes up to replace the lost base, which stops the anion gap from widening. That makes the chloride shift a key clue in separating acid loss from acid accumulation.
Some toxins can also produce unusual patterns or mixed disorders. Because toxin-related states may change quickly, a single calculator result should not be used in isolation. Instead, it should be interpreted with the patient’s symptoms, medication exposures, renal function, and the full electrolyte panel.
Limitations of an Anion Gap Calculator
An anion gap calculator is practical, but it has restrictions. One major issue is laboratory variation. Different analyzers and reporting methods can alter the reference range, especially when potassium is added or omitted. A result that appears abnormal in one context may be appropriate in another.
Testing error can also distort the result. Slight inaccuracies in sodium, chloride, or bicarbonate may change the gap enough to influence interpretation. This is particularly important when values are near the limit or when a patient has unusual clinical physiology, such as severe dehydration, marked protein abnormalities, or mixed acid-base states.
A further restriction is that the calculator does not reveal the reason of the problem. It can suggest that the numbers suggest an acid base issue, but it cannot determine whether the issue is lactic acid buildup, ketoacidosis, renal failure, poison exposure, or reduced bicarbonate. It requires a history, exam, and additional testing.
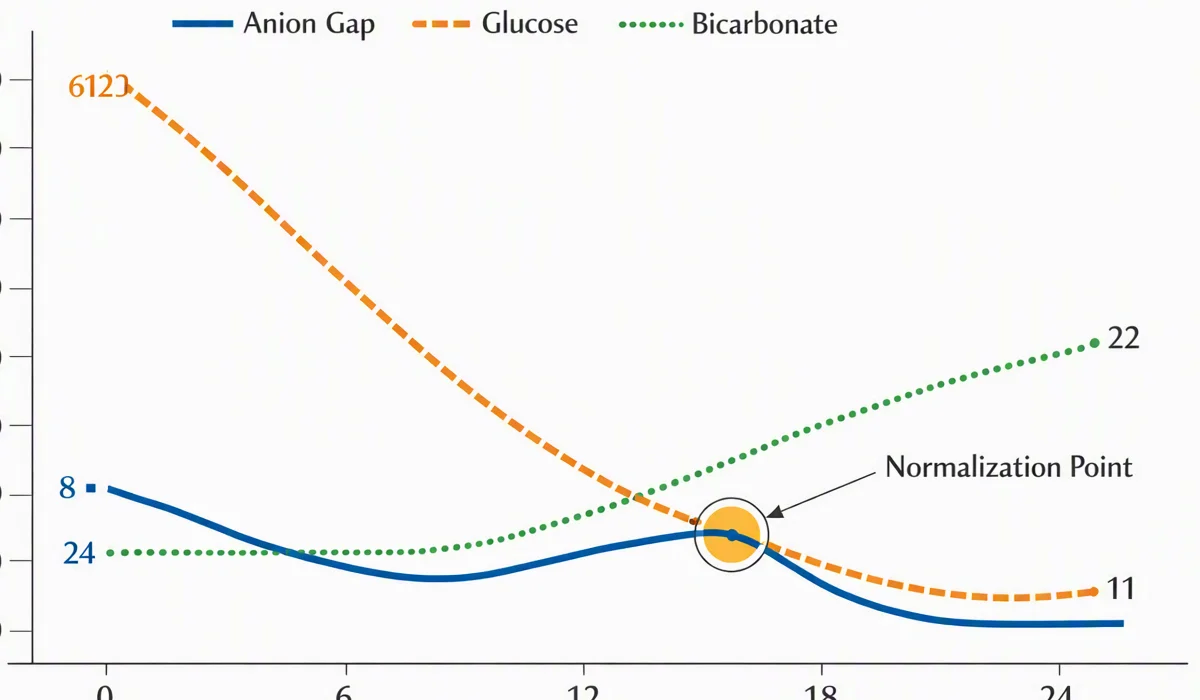
For these reasons, clinical judgment is still essential. This calculator works best as a helping tool for clinical interpretation, not an alternative for complete evaluation. If the results do not match the patient’s condition, recheck the entered values, verify the sample, and consider the wider context.
FAQ About Anion Gap and Chloride Shift
What is an anion gap calculator used for?
An anion gap calculator is applied to estimate the difference between recorded cations and anions in blood chemistry. It aids check acid-base balance, detect possible metabolic acidosis, and guide review of an acid-base disorder using measurements such as sodium, chloride, and bicarbonate.
How does chloride shift affect the anion gap?
The shift in chloride may offset loss of bicarbonate by raising chloride, which may maintain the anion gap normal even when acidosis is present. This is why a pattern of increasing chloride with decreasing bicarbonate often suggests a normal anion gap acidosis, while a gap rise without chloride replacement suggests a raised-gap process.
What’s the normal anion gap range?
The normal anion gap is influenced by the lab and whether potassium is included in the formula. Some labs use a range around 8 to 12 mEq/L, but the exact reference range should still match the local method and reporting format.
How do albumin levels change the anion gap?
Albumin is a important unmeasured anion, so low albumin lowers the measured gap. In hypoalbuminemia, the raw result may miss the true acid load, which is why albumin correction is important for accurate interpretation.
When should a high anion gap be considered urgent?
A high gap may be urgent when it is associated with severe symptoms, rapid breathing, altered mental status, shock, or suspected lactic acidosis, ketoacidosis, renal failure, or toxins. In those settings, prompt evaluation with arterial blood gas, serum electrolytes, and full clinical assessment is necessary.